
Pancreatic Neuroendocrine Tumor (PNET)
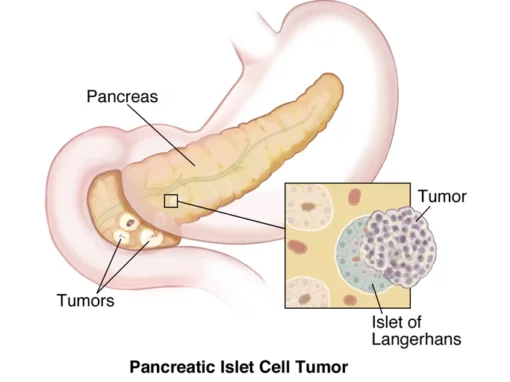
Pancreatic neuroendocrine tumor (PNET) is defined as islet cell tumors of the pancreas that make islet cell type hormones. PNET can be functional or non-functional.
Functional: (means the tumor made hormones cause symptoms and show elevation)
- Insulinoma, Gastrinoma, Glucagnoma, VIPoma
- Most functional are more benign but still difficult to predict behavior and require close follow up.
Non-functional: (hormones released do not cause symptoms or no elevation of hormone at all)
- Does not see elevation of or hyperhormonal symptoms
- Most non-functional are more malignant (determined based on metastasis) because difficult to predict behavior.
Cause and risk factors/Association:
- MEN1 gene mutation has been associated with increased risk of endocrine tumors
Symptoms and Diagnosis of Pancreatic Neuroendocrine Tumors:
Non-functional:
- Indigestion, diarrhea, epigastric/abdomen pain, jaundice, palpable mass at right upper quadrant that is usually non-tender.
Functional
- Symptoms of excess hormones production depending on the type of hormones being excessively produced
- Insulinoma:
- Usually benign solitary (arise from beta cells), elevated insulin levels
- Hypoglycemia especially post fasting and relieved with glucose in take
- Whipple Triad (Low sugar, Hypoglycemia Symptoms, Reversal of Symptoms with Glucose)
- Gastrinoma (ZES): see ZES section
- Multiple ulcers (esophagus, stomach, duodenum, jejunum), elevated gastrin levels.
- Can also arise from duodenum and peripancreatic tissues
- Hypergastrenemia with ulcers refractory to conventional treatment.
- Zollinger Ellison Syndrome (ZES): multiple duodenal ulcer, steatorrhea, prominent gastric rugal fold due to increase oxyntic gland mass
- VIPoma
- Tumors cells that produce excess VIP (vasoactive intestinal peptide)
- Achlorhydria (low acid secretion from VIP);
- Vasodilation (flushing, hypotension), nausea vomiting, weakness.
- Hyperglycemia (due to increased glycogenolysis), hypercalcemia (due to increased bone resorption)
- Watery Diarrhea with hypokalemia (hence muscle weakness), hypotension (due to loss volume).
- Increased potassium secretion
- Labs: stool studies show Osmolar gap < 50mOsm/kg, increased potassium ( Na+)
- Diagnosis: VIP > 75 pg/ml confirms and watery diarrhea). CT abdomen (pancreatic lesion usually found on the tail of pancreas)
Lab Markers and Morphological features
- See hormones for Functional PNET
Progression and Course of Disease
- Hard to predict and need close monitoring.
Treatment and Management
- Surgical resection for localized lesion (whipple procedure)
- Some patient can choose the wait and watch approach if the lesion does not show aggressive behavior.
- Chemotherapy if metastatic.